
Medically reviewed by Mufaddal M. Gombera, MD, Board-Certified Orthopedic Surgeon.
Dr. Mufaddal Gombera is board-certified in orthopedic surgery with subspecialty certification in sports medicine, and he has managed acute dislocations from the sideline to the operating room as a team physician for collegiate and professional athletes. If your shoulder came out of its socket, getting it back in is only step one. What you do in the following weeks, and whether you get a real risk assessment, largely determines whether this happens again.
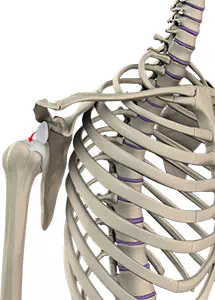
What Happens When a Shoulder Dislocates
A dislocated shoulder means the ball at the top of your arm bone was forced completely out of the socket in your shoulder blade. About 95 percent of dislocations are anterior, meaning the ball comes out the front, usually from a fall, tackle, or forced overhead twist. Coming out is not gentle: the ball typically tears the labrum, the cartilage rim that seals the socket, at its front edge. That injury is called a Bankart tear. The ball itself can also be dented against the socket rim, and ligaments and capsule are stretched. This structural damage is why dislocated shoulders can become unstable shoulders.
Putting It Back In: Reduction
Reduction is the maneuver that guides the ball back into the socket, and it should be done by a trained clinician after an X-ray whenever possible. In the emergency room, you receive medication to relax the muscles, the joint is gently relocated, and a second X-ray confirms position and screens for fracture. Relief is usually immediate and dramatic, though the shoulder stays sore. Do not let a well-meaning teammate yank on your arm: poorly performed reductions can break bone or injure nerves.
Aftercare: The First Weeks
Aftercare has three goals: let the irritated joint settle, restore motion, then rebuild the strength that protects against another dislocation. A typical plan looks like this:
- Sling for comfort, usually one to four weeks. Younger patients are often braced slightly longer, older patients are mobilized sooner to avoid stiffness.
- Ice and pain control for the first several days.
- Early gentle motion, starting within the first one to two weeks.
- Progressive physical therapy for the rotator cuff and shoulder blade muscles, typically 6 to 12 weeks.
- Gradual return to sport or heavy work, sometimes with a brace for contact athletes.
Will It Happen Again? Recurrence Risk by Age
Age at the first dislocation is the strongest predictor of whether your shoulder dislocates again. In athletes under 20, studies report recurrence rates as high as 80 to 90 percent without surgical stabilization, particularly in contact and overhead sports. Through the 20s and 30s the risk falls but remains meaningful. Over 40, re-dislocation becomes uncommon, but the same injury tears the rotator cuff in a substantial share of patients, so lingering weakness after a dislocation in this group needs a rotator cuff tear workup. Each repeat dislocation can wear away bone from the socket rim, and enough bone loss changes the required surgery from a simple repair to a bone transfer procedure. Preventing the second and third dislocation is exactly the point of an early specialist visit.
When to See a Surgeon After a First Dislocation
See an orthopedic surgeon within the first one to two weeks after any first dislocation, not because everyone needs surgery, but because this is when the risk discussion changes outcomes. Dr. Gombera reviews your age, sport, job demands, exam, and imaging, and lays out both paths honestly. For a 17-year-old linebacker, early arthroscopic Bankart repair is a reasonable first-line option given the recurrence numbers. For a 55-year-old who slipped on a wet floor, structured rehab is usually right, with an MRI if weakness persists. Patients with repeat dislocations, or bone loss on imaging, are candidates for the broader menu of shoulder instability surgery. You should leave the visit knowing your personal recurrence risk, not a generic one.
Discover Your Ortho Options
When to Seek Care Right Away: Red Flags
Certain symptoms after a dislocation need urgent attention rather than watchful waiting:
- A shoulder that is still visibly out of place, or that you cannot move
- Numbness, tingling, or a cold, pale hand, which can signal nerve or vessel injury
- Severe pain that is worsening rather than easing after reduction
- Inability to lift the arm, or weakness persisting beyond two to three weeks
- Repeat slipping or dislocation during normal activities
A dislocation handled well the first time, with an honest risk assessment, is your best protection against a shoulder that dislocates for years.
Frequently Asked Question
Can I pop a dislocated shoulder back in myself?
No, do not try. Forcing a dislocated shoulder can fracture bone or injure the nerves and vessels that run near the joint. Go to an emergency room or urgent care, where the joint can be relocated after an X-ray confirms the direction of the dislocation and rules out fracture. Trained team physicians sometimes reduce shoulders on the sideline, but self-reduction risks real harm.
How long do I wear a sling after a shoulder dislocation?
Typically one to four weeks, depending on your age and injury. The sling is for comfort and early protection, not a cure, and wearing it longer does not meaningfully lower the chance of another dislocation. Gentle motion usually starts within days to prevent stiffness, followed by progressive strengthening. Older patients start moving sooner because they stiffen faster.
Does a first shoulder dislocation need surgery?
Not always, and the honest answer depends mostly on age and sport. Young contact athletes have a very high redislocation risk, so early stabilization is a reasonable first-line option for them. Older and lower-demand patients usually start with rehabilitation. Every first-time dislocator deserves an individualized risk discussion rather than a blanket rule either way.
When can I return to sports after a dislocated shoulder?
Without surgery, many athletes return in two to six weeks once motion and strength recover, sometimes with a brace, but the redislocation risk in season is real and should be discussed openly. After stabilization surgery, contact sport typically waits 4 to 6 months. The right timeline balances your season, position, and how much risk you are willing to accept.
Why is my arm still weak weeks after a dislocation?
Persistent weakness is not normal soreness and should be examined. In patients over 40, a dislocation frequently tears the rotator cuff, and that tear, not the dislocation itself, causes lasting weakness. Nerve stretch injuries, especially of the axillary nerve, can also cause weakness and numbness. Both problems change the treatment plan, so tell your surgeon promptly.
What is the difference between a dislocation and a subluxation?
A dislocation is a complete separation: the ball leaves the socket entirely and usually needs to be put back in. A subluxation is a partial slip in which the ball slides to the rim and returns on its own. Both stretch or tear the stabilizing structures, and repeated subluxations are a form of shoulder instability worth evaluating.
Schedule an Evaluation After Your Shoulder Dislocation in Houston
Recent dislocation? Dr. Gombera offers same-week consultations at Texas Orthopedic Hospital (7401 Main St), the Memorial office (8731 Katy Freeway, Suite 110), and the Baytown office (7718 Garth Rd).

