
Medically reviewed by Mufaddal M. Gombera, MD, Board-Certified Orthopedic Surgeon.
Dr. Mufaddal Gombera is board-certified in orthopedic surgery with subspecialty certification in sports medicine, and frozen shoulder is one of the conditions where his advice is most often reassuring: the overwhelming majority of frozen shoulders resolve without surgery. If your shoulder has grown painful and then progressively stiff, seemingly out of nowhere, this page explains the three phases, honest timelines, and what helps at each stage.
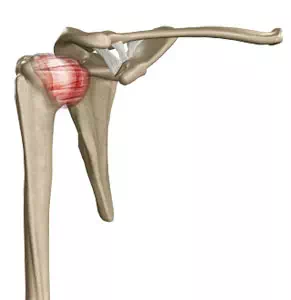
What Is Frozen Shoulder?
Frozen shoulder, medically called adhesive capsulitis, is a condition in which the capsule surrounding the shoulder joint becomes inflamed, thickens, and contracts, painfully restricting motion in every direction. The capsule is the flexible envelope that normally lets the ball glide freely in the socket. When it scars down, the shoulder loses motion even when someone else tries to move it for you, the hallmark that separates frozen shoulder from tendon problems. It usually arrives without any injury at all.
The Three Phases of Frozen Shoulder
Frozen shoulder moves through three predictable phases, and the full course commonly runs 1 to 2 years, sometimes longer. Knowing your phase sets realistic expectations and determines which treatment helps.
- Freezing (roughly 2 to 9 months). Pain dominates. The shoulder aches constantly, sleep suffers, and motion gradually shrinks. This phase is most often mistaken for a rotator cuff problem.
- Frozen (roughly 4 to 12 months). Stiffness dominates. Pain often eases, but reaching overhead, behind your back, or out to the side hits a firm wall. Fastening a bra, tucking in a shirt, or reaching a seatbelt becomes the real problem.
- Thawing (roughly 6 months to 2 years). Motion slowly returns as the capsule remodels. Most people regain functional, comfortable motion, though the last few degrees take their time.
Diabetes and Other Risk Factors
Frozen shoulder has a strong association with diabetes, and people with diabetes tend to have more severe, longer-lasting cases. Diabetes raises the risk several-fold, and frozen shoulder in a diabetic patient can affect both shoulders over time. Other risk factors include thyroid disorders, age 40 to 60, female sex, and any stretch of shoulder immobility after a fracture, surgery, or long sling use. If you have diabetes and a stiffening shoulder, do not wait for it to pass; seek care early.
How Dr. Gombera Diagnoses Frozen Shoulder
Frozen shoulder is diagnosed by examination, and the defining finding is lost passive motion: the shoulder will not rotate or elevate even when Dr. Gombera moves it gently for you. That single finding separates it from a rotator cuff tear, where assisted motion stays free. X-rays rule out shoulder arthritis, which also stiffens the joint but shows clear changes on X-ray, while frozen shoulder X-rays look normal. MRI is rarely needed. If your main symptom is pain with overhead reach rather than global stiffness, the problem may be shoulder impingement instead.
Discover Your Ortho Options
Treatment: What Dr. Gombera Offers at Each Phase
The honest headline: most frozen shoulders resolve with time, therapy, and injections; treatment shortens the course and makes it less miserable. Dr. Gombera matches treatment to phase:
- Freezing phase. Calm the inflammation. A cortisone injection into the joint, ideally early, reliably reduces pain and can shorten this phase. Medication and gentle motion round out the plan. Aggressive stretching now usually backfires.
- Frozen phase. Shift to motion. Progressive stretching with therapy and a home program does the heavy lifting. For stubborn cases, hydrodilatation, an image-guided injection that expands the capsule with fluid, can help unlock motion.
- Thawing phase. Therapy consolidates returning motion and rebuilds strength lost during the stiff months.
Do I Need Surgery for Frozen Shoulder?
Rarely, and that is worth saying plainly: surgery is the exception in frozen shoulder, reserved for the small minority whose stiffness stays disabling despite months of proper treatment. When justified, Dr. Gombera performs an arthroscopic capsular release through shoulder arthroscopy, dividing the contracted capsule through small incisions, with immediate therapy afterward to keep the regained motion. Patients with diabetes are somewhat more likely to need a release, but even then, most never do. If a surgeon offers a capsular release in the first months of a freezing shoulder, a second opinion is reasonable.
When to See a Doctor
See a doctor when shoulder stiffness starts limiting daily tasks, and sooner if pain is disturbing sleep, because early-phase treatment is the most effective window. Seek prompt evaluation if stiffness follows a fall, if you have diabetes and new shoulder symptoms, if your problem is weakness more than stiffness, or if you have fever, redness, or weight loss, which point away from frozen shoulder. You do not need a year of poor sleep waiting for a diagnosis an examination makes in one visit.
Discover Your Ortho Options
Frequently Asked Question
How long does frozen shoulder last?
Longer than most people expect: commonly 1 to 2 years from first pain to comfortable motion, and sometimes longer, particularly in patients with diabetes. The flip side: the condition is self-limited, resolving in the great majority of people. Treatment exists to shorten the painful phase and protect motion, not because the shoulder would never recover.
Why did I get frozen shoulder?
Often there is no clear reason. The capsule around the joint becomes inflamed, thickens, and contracts. Known risk factors include diabetes, thyroid disease, age between 40 and 60, being female, and a period of shoulder immobility after injury or surgery. It is not caused by something you did, and it is not arthritis.
Should I push through the pain to stretch a frozen shoulder?
Gentle, frequent stretching helps; aggressive, painful cranking does not. During the early inflamed phase, forcing motion tends to increase inflammation and pain without gaining range. The better strategy is calming inflammation first, often with an injection, then stretching progressively as the shoulder allows. Effort matters, but timing that effort to the phase matters more.
Do cortisone injections help frozen shoulder?
Yes, especially early. An injection into the joint during the freezing phase reliably reduces pain and, given with physical therapy, can shorten the painful stage and improve early motion. Cortisone works best in the first few months of symptoms, a strong argument for an early diagnosis.
Will my frozen shoulder come back?
Recurrence in the same shoulder is uncommon once the process fully resolves. However, roughly 1 in 5 patients eventually develops frozen shoulder on the opposite side, and the risk is higher in people with diabetes. If your other shoulder begins hurting and stiffening the same way, seek treatment early, because early-phase care is the most effective.
How do I know it is frozen shoulder and not a rotator cuff tear?
The key difference is passive motion. With frozen shoulder, the arm will not move even when someone else gently lifts it, because the capsule itself is contracted. With a rotator cuff tear, someone else can usually raise your arm normally, but you are weak lifting it yourself. An examination separates the two quickly.
Schedule a Frozen Shoulder Evaluation in Houston
Dr. Gombera treats frozen shoulder at Texas Orthopedic Hospital (7401 Main St), the Memorial office (8731 Katy Freeway, Suite 110), and the Baytown office (7718 Garth Rd). Same-week consultations are available, and early treatment works best.
