
Medically reviewed by Mufaddal M. Gombera, MD, Board-Certified Orthopedic Surgeon.
Dr. Mufaddal Gombera is board-certified in orthopedic surgery with subspecialty certification in sports medicine, and impingement is one of the most common problems he treats in active adults. If it hurts to reach overhead, behind your back, or across your body, impingement is a likely culprit. The good news is worth stating up front: most people with shoulder impingement get better without surgery.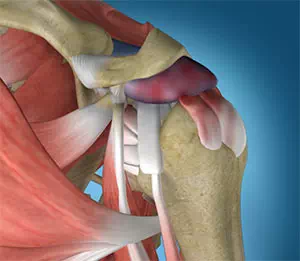
What Is Shoulder Impingement?
Shoulder impingement means the rotator cuff tendons and their cushioning sac get pinched in the narrow space at the top of your shoulder each time you raise your arm. Between the ball of the shoulder and the bony roof above it, called the acromion, sits about a centimeter of space occupied by the rotator cuff tendons and the bursa, a thin fluid-filled cushion. When that tissue swells from overuse, injury, or poor mechanics, the space shrinks. Every overhead reach then pinches the swollen tissue, creating more swelling that feeds the cycle. Swimmers, throwers, painters, and lifters know this pattern well, but anyone can develop it.Impingement or a Rotator Cuff Tear?
Impingement and rotator cuff tears sit on the same spectrum, and the practical difference is weakness. Impingement hurts, especially with overhead reach, but strength is largely preserved once pain is controlled. A rotator cuff tear more often causes true weakness, night pain that will not settle, and trouble lifting the arm against light resistance. The distinction matters because long-standing impingement can keep the tendon inflamed and contribute to fraying and partial tearing. After a fall or a pop followed by weakness, treat it as a possible tear and get examined promptly.
Symptoms of Shoulder Impingement
Impingement pain follows a recognizable pattern tied to arm position. Typical symptoms include:
- Pain when raising the arm, especially between shoulder height and overhead
- A painful arc: comfortable at the start of the lift, painful in the middle, easier at the top
- Pain reaching behind your back, into a jacket sleeve, or across your body
- An ache along the outer shoulder and upper arm after activity
- Night discomfort when lying on the affected side
How Dr. Gombera Diagnoses Impingement
Diagnosis is made primarily by examination, with imaging used to rule out other problems. Specific positions reproduce the pinch, and strength testing separates guarding from genuine weakness. X-rays show the shape of the acromion, bone spurs, and any arthritis. An MRI is added when night pain, weakness, or a poor response to treatment raises suspicion for a tear. Occasionally a numbing injection into the bursa is both treatment and confirmation of the diagnosis. When symptoms do not fit, Dr. Gombera looks deliberately for the mimics, including frozen shoulder and neck-related pain, using our shoulder pain guide patterns rather than defaulting to the common answer.
Discover Your Ortho Options
Treatment: Conservative First, Almost Always
Most shoulder impingement improves without surgery, and that is the plan Dr. Gombera starts with. The ladder looks like this:
- Relative rest. Pause the specific overhead activities that provoke pain. Total rest is not required.
- Physical therapy. The cornerstone: 6 to 12 weeks of rotator cuff strengthening, shoulder blade control, and posture work to reopen the pinched space mechanically.
- Anti-inflammatory medication. Short courses to interrupt the swelling cycle.
- Cortisone injection. For pain that blocks sleep or therapy, almost always paired with continued rehab.
Most patients feel meaningful improvement within about six weeks and return to full activity within three months.
Do I Need Surgery for Impingement?
The honest answer: only a small minority of impingement patients ever need surgery. Dr. Gombera considers shoulder arthroscopy when a well-executed conservative program has failed over roughly three to six months, or when imaging reveals a structural problem such as a significant spur or a tendon tear. The procedure removes inflamed bursa and any spur narrowing the space, and addresses tendon damage found at the same time. Surgery for pure impingement has become deliberately less common as evidence has shown how well structured rehab performs, and Dr. Gombera follows that evidence.
Discover Your Ortho Options
When to See a Doctor: Red Flags
See a doctor promptly rather than waiting out your symptoms if any of these apply:
- Sudden weakness, or pain that began with a fall, jerk, or pop, which suggests a tear
- Night pain persisting beyond two to three weeks despite rest and medication
- Rapidly progressive stiffness, which points toward frozen shoulder
- Numbness or tingling into the arm or hand, which suggests a nerve or neck problem
- No improvement after four to six weeks of honest conservative care
Impingement caught early is one of the most fixable problems in the shoulder. The same symptoms ignored for a year are a much harder project.
Frequently Asked Question
Can shoulder impingement heal on its own?
Often, yes, with the right help. Impingement is an irritation problem, not a torn structure, so calming the inflammation and correcting the mechanics that caused it usually resolves symptoms. Simple rest alone helps less than people expect, because the underlying strength and posture issues remain. A structured therapy program is what changes the outcome.How long does shoulder impingement take to get better?
Most patients improve meaningfully within 6 to 12 weeks of consistent physical therapy, though shoulders that have been irritated for months can take longer. Improvement usually comes gradually, week by week. If a dedicated program produces no progress after about three months, the right move is to re-examine the diagnosis, not to push harder.Is impingement the same thing as bursitis or tendinitis?
They overlap. Impingement describes the mechanical pinching of tissue in the narrow space at the top of the shoulder. Bursitis means the cushioning sac in that space is inflamed, and tendinitis means the rotator cuff tendon itself is irritated. In practice they occur together, and the treatment, calming inflammation and restoring mechanics, is largely the same.Will a cortisone shot cure my impingement?
A cortisone injection can break the pain cycle, but it rarely fixes impingement by itself. The injection quiets the inflamed bursa so you can sleep and do therapy effectively; the therapy is what corrects the mechanics that caused the pinching. Dr. Gombera typically pairs an injection with a rehab plan instead of offering it as a stand-alone fix.What exercises help shoulder impingement?
Programs that strengthen the rotator cuff with the arm below shoulder height, plus exercises improving shoulder blade control and posture, form the core of treatment. Rows, external rotation work, and scapular stability drills are common examples, while painful overhead pressing is paused early on. A physical therapist tailors the details so you strengthen without re-irritating the tissue.What happens if impingement is ignored?
Long-standing impingement can keep the rotator cuff inflamed and, over time, contribute to fraying and partial tearing of the tendon. Untreated shoulders also tend to stiffen as people avoid using them. Neither outcome is inevitable, but months of persistent symptoms deserve evaluation, because early treatment is simpler and more successful than treating an established tear.Closing CTA block
Schedule a Shoulder Impingement Evaluation in Houston
Dr. Gombera treats shoulder impingement at Texas Orthopedic Hospital (7401 Main St), the Memorial office (8731 Katy Freeway, Suite 110), and the Baytown office (7718 Garth Rd). Same-week consultations are available.

